
Shoulder impingement
Shoulder impingement is a common name for pain at the top and outer shoulder that catches as you lift the arm or reach overhead. It usually comes from sensitive rotator cuff tendons and the bursa that sits over them. Most people improve with activity changes and a steady strengthening program.
At the Specialist Orthopaedic Surgery Clinic in East Melbourne, orthopaedic assessment, physiotherapy, myotherapy and strength testing are all in the same rooms, so the reason your shoulder pinches can be worked out and treated in one place.

What is shoulder impingement?
The rotator cuff tendons run under a bony arch at the top of the shoulder, with a thin cushion called the subacromial bursa between them. As the arm lifts, these tissues glide under the arch.
When the tendons or bursa become sensitive, lifting the arm through the middle of its range can cause a sharp, pinching pain. Clinicians often call this subacromial pain. The tendon is usually irritated and less able to handle load, and in most cases it is not being worn away or torn.
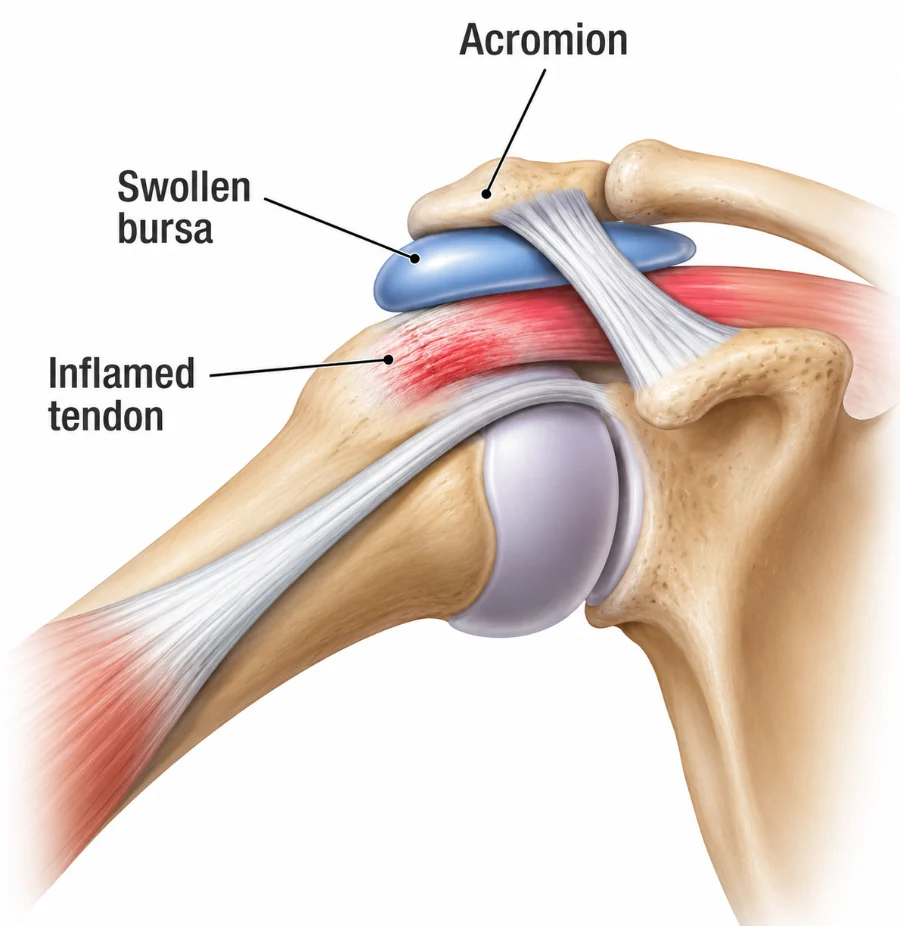
Does this sound like you?
Arrange an assessment if the pinching pain keeps returning, disturbs sleep, limits work or exercise, or has not settled after several weeks of sensible activity changes and exercise.
How it is diagnosed
Diagnosis is based on how the pain started and which movements bring it on. Shoulder movement and strength are tested in several positions, and the neck is checked because neck problems can refer pain to the shoulder.
Imaging is often not needed at first. Ultrasound or MRI may be arranged if weakness is marked, pain persists despite good rehabilitation, or a tendon tear is suspected. Tendon and bursa changes on a scan are common in people without pain, so results are always matched to the examination.
Treatment and recovery
Treatment aims to calm the irritated tendon and bursa, then build strength so the shoulder can handle overhead work again. Most people improve without surgery.
First weeks
Settle the pain
Repeated overhead lifting and painful reaching are reduced for a while, but the arm keeps moving within comfort. Short-term pain relief can be discussed with your GP or pharmacist.
Physiotherapy
Build control
Exercises strengthen the rotator cuff and shoulder blade muscles so the arm lifts more smoothly. Myotherapy may ease tight neck and shoulder muscles alongside exercise.
Building up
Return to overhead tasks
Exercises move gradually higher and heavier towards your work, gym or sport. Strength testing can show when the shoulder is ready.
If pain persists
Review the plan
If pain still limits you after a well-structured program, the diagnosis is reviewed and further imaging or an injection may be considered. Injections are not given at the clinic. If one is recommended, your GP can arrange it, usually through a radiology practice.
Exercises you may be given
Your physiotherapist will choose the right ones and the right level for you.
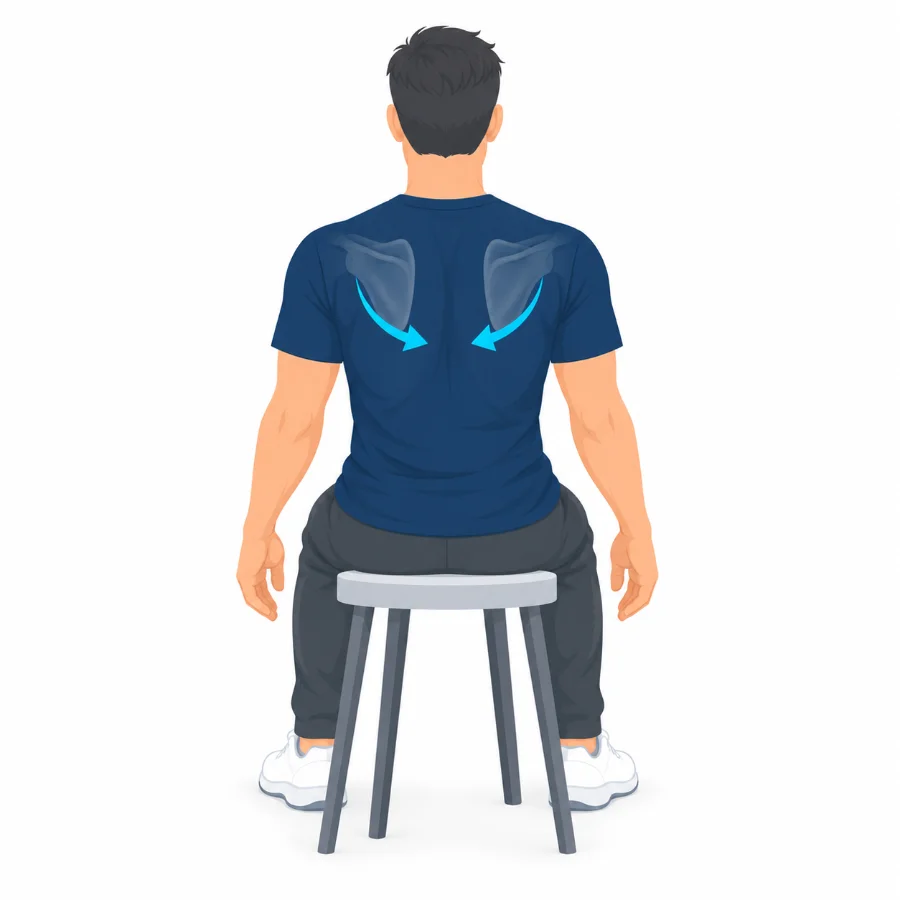
Shoulder blade squeeze
Sit or stand tall. Draw your shoulder blades gently back and down, hold, then relax without shrugging.
10 holds of 5 seconds

Outward press against a wall
Stand side-on to a wall with your elbow bent and tucked in. Press the back of your hand gently into the wall without moving. Hold, then relax.
5 holds of 20 to 30 seconds
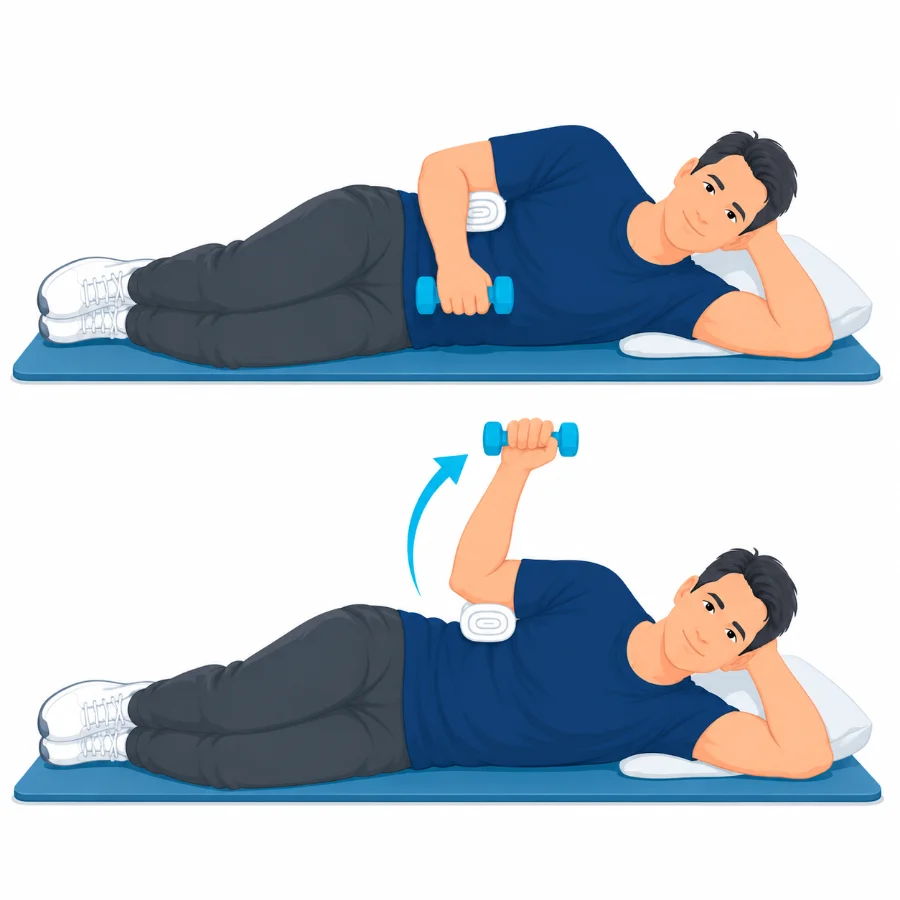
Side-lying rotation
Lie on your good side with a small towel under the elbow. Slowly turn the forearm up with a light weight, then lower it.
2 to 3 sets of 10, slow
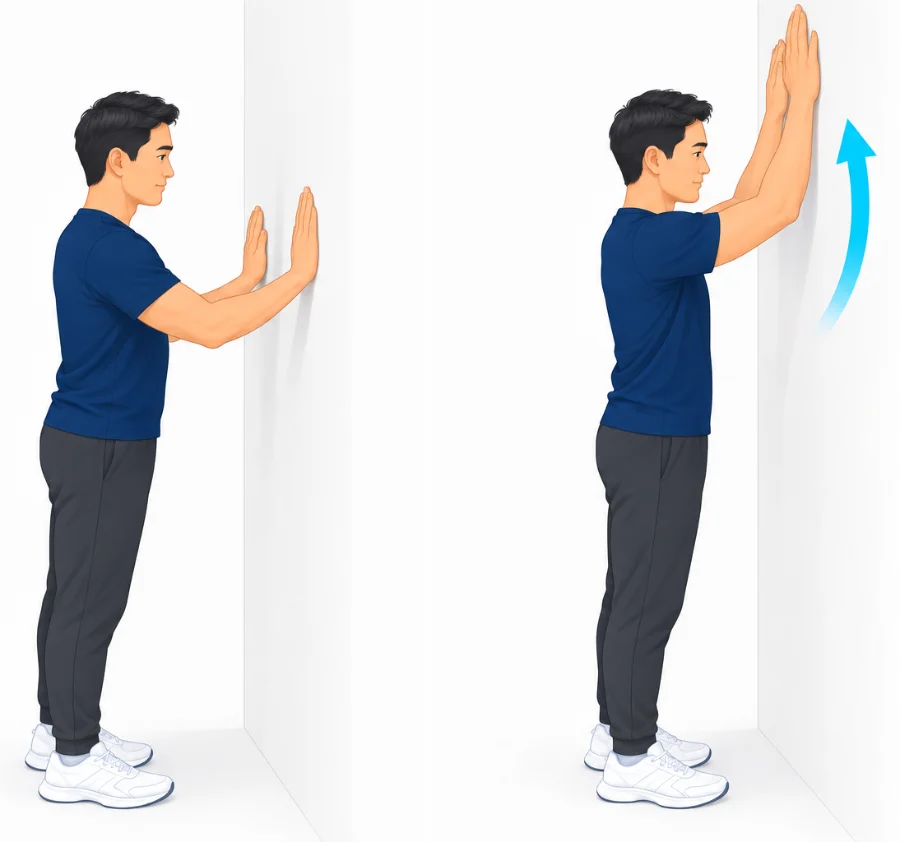
Wall slides
Face a wall with your forearms resting on it. Slowly slide your arms up the wall as far as is comfortable, then slide back down.
10 slow slides, once or twice a day
Other treatment options
Injections
A subacromial corticosteroid injection may ease pain for a time when it is stopping useful rehabilitation. The benefit is usually temporary and repeated injections are generally avoided.
When surgery is needed
Arthroscopic subacromial decompression may be considered only rarely, when pain remains substantial despite a well-structured rehabilitation program and a clear treatable cause is found. The shape of the bone on a scan is not enough by itself to justify an operation. Prof Phong Tran performs subacromial decompression, and his website explains the options and recovery.
Common questions
Is my tendon being worn away by the bone?
Usually not. The tendon and bursa are sensitive and less able to handle load. Strengthening helps them cope again.
Is impingement the same as a rotator cuff tear?
No. Impingement pain usually comes from an irritated tendon and bursa without a tear, although the two can occur together.
Should I stop using my arm?
No. Complete rest is rarely needed. Painful overhead tasks are reduced for a while and strength is rebuilt gradually.
Do I need a scan?
Usually not at first. Ultrasound or MRI is considered if weakness is marked, symptoms persist or another problem is suspected.
Will I need decompression surgery?
Rarely. Most people improve with exercise and activity changes, and surgery is reserved for a small number with a clear treatable cause.
Book an assessment
An assessment can confirm why your shoulder pinches and set out a plan to get you reaching comfortably again. Physiotherapy with A/Prof Amir Takla and Imogen Clark, myotherapy with Joanne VanDer Haar, and specialist review with Prof Phong Tran, all at 166 Gipps Street, East Melbourne. Please bring any previous scan reports and details of physiotherapy or injections already tried.