
Patellofemoral arthritis
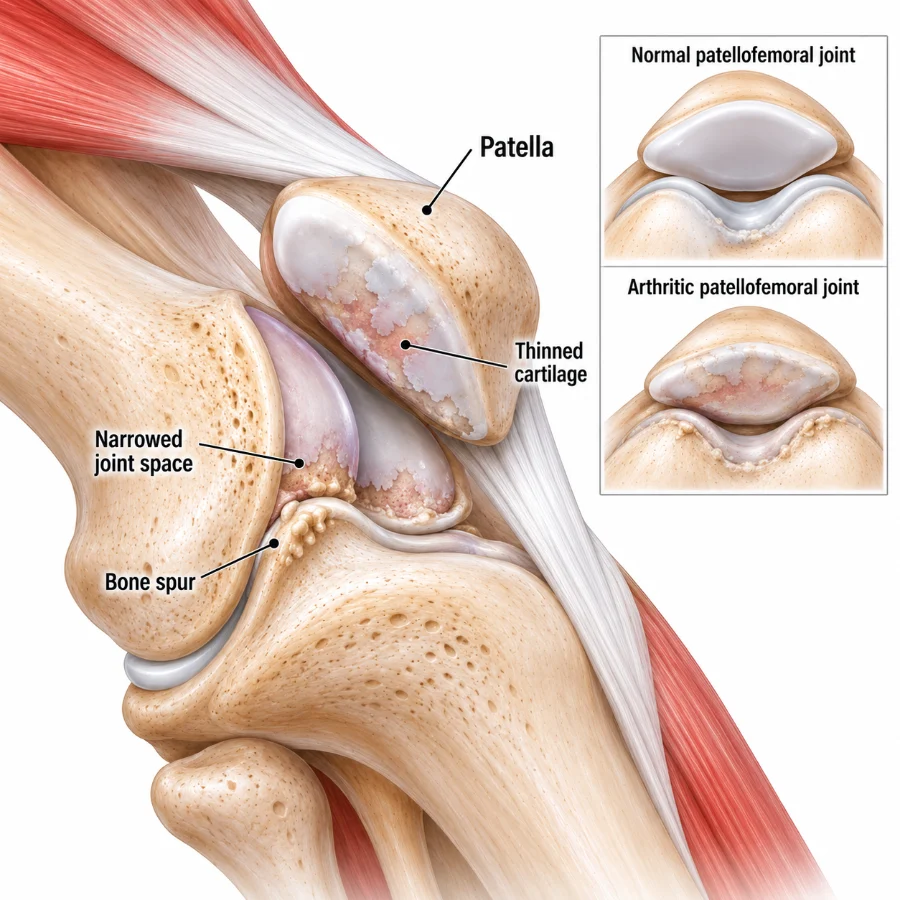
Patellofemoral arthritis is wear of the cartilage behind the kneecap. It often causes pain at the front of the knee with stairs, squatting, kneeling or getting up from a chair. Many people improve with thigh and hip strengthening and sensible changes to how they load the knee.
At the Specialist Orthopaedic Surgery Clinic in East Melbourne, orthopaedic assessment, physiotherapy, myotherapy and strength testing are all under one roof, so your program can be matched to your kneecap and the tasks you find hardest.

What is patellofemoral arthritis?
The patellofemoral joint is where the kneecap glides in a groove at the front of the thigh bone. Smooth cartilage lines both surfaces, and the thigh muscles guide the kneecap as the knee bends and straightens.
In patellofemoral arthritis this cartilage gradually wears. The joint behind the kneecap takes more load when the knee is bent under body weight, which is why stairs, squats and low chairs are often the hardest tasks. It may occur alone or with arthritis in other parts of the knee.
Does this sound like you?
Arrange an assessment if pain at the front of the knee is limiting stairs, squatting or getting up from a chair, keeps coming back, or has not improved with a suitable exercise program. Review is also worthwhile if swelling keeps returning or the kneecap feels unstable.
How it is diagnosed
Diagnosis starts with where the pain is and which tasks bring it on. Kneecap movement and tracking, knee and hip strength, flexibility, walking, squatting and stairs are checked.
X-rays confirm the arthritis and show whether other parts of the knee are also worn. MRI is not routinely needed, but it may help when the diagnosis is unclear or a cartilage injury is suspected. Strength testing can find weakness and guide the program.
Treatment and recovery
Treatment aims to ease pain and rebuild the strength needed for stairs, squatting and rising from a chair. It usually combines a period of lighter load on the kneecap with steady quadriceps and hip strengthening.
First steps
Adjust the load
Stairs, deep squats, kneeling and low seats are reduced for a time, while walking, cycling or swimming keep the knee active.
Physiotherapy
Build strength
Quadriceps, hip and calf strengthening in comfortable ranges, with taping or other supports if helpful. Myotherapy can ease nearby muscles.
Building up
Return to tasks
Stairs, squatting and other daily tasks are rebuilt gradually. Strength testing can track progress.
If symptoms stay severe
Review the plan
Pain relief or an injection may be reviewed, and surgical options may be discussed in selected severe cases. Injections are not given at the clinic. If one is recommended, your GP can arrange it, usually through a radiology practice.
Exercises you may be given
Your physiotherapist will choose the right ones and the right level for you.
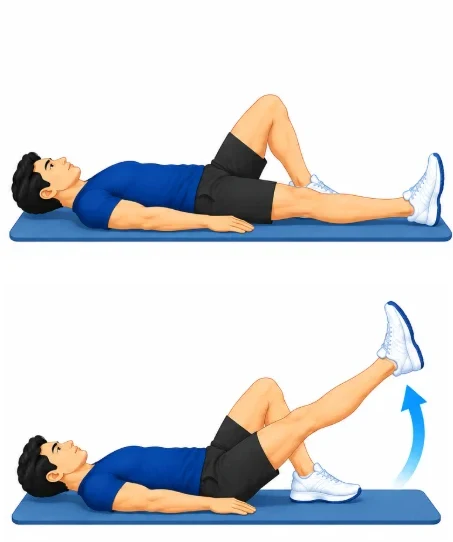
Straight leg raise
Lie on your back with the other knee bent. Tighten the thigh of the sore leg, keep it straight and lift it to the height of the bent knee, then lower slowly.
2 sets of 10
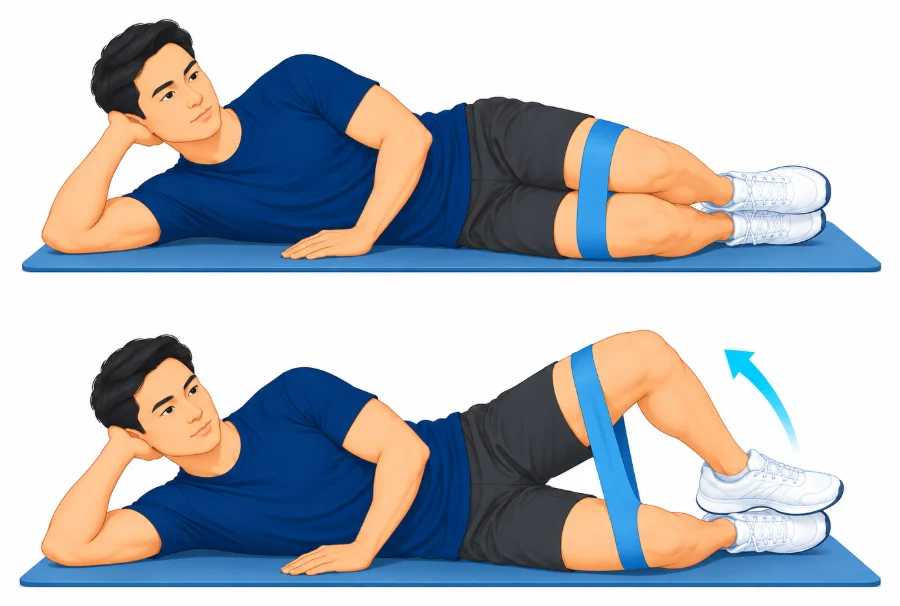
Clam
Lie on your side with the sore leg on top, knees bent and heels together. Keep your feet touching and lift the top knee, then lower slowly.
2 sets of 10 to 15
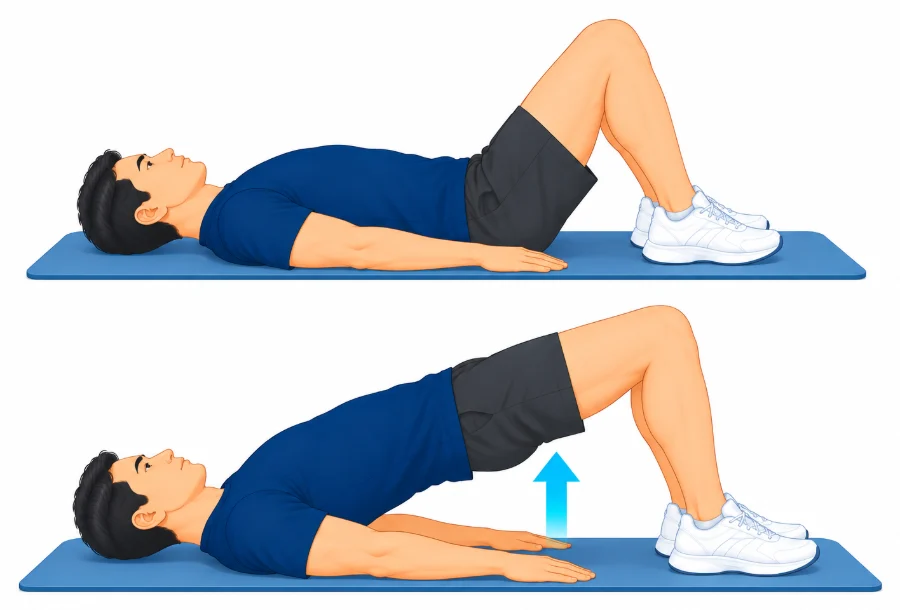
Bridge
Lie on your back with knees bent and feet flat. Squeeze your buttocks and lift your hips until your body is in a straight line, then lower slowly.
2 sets of 10
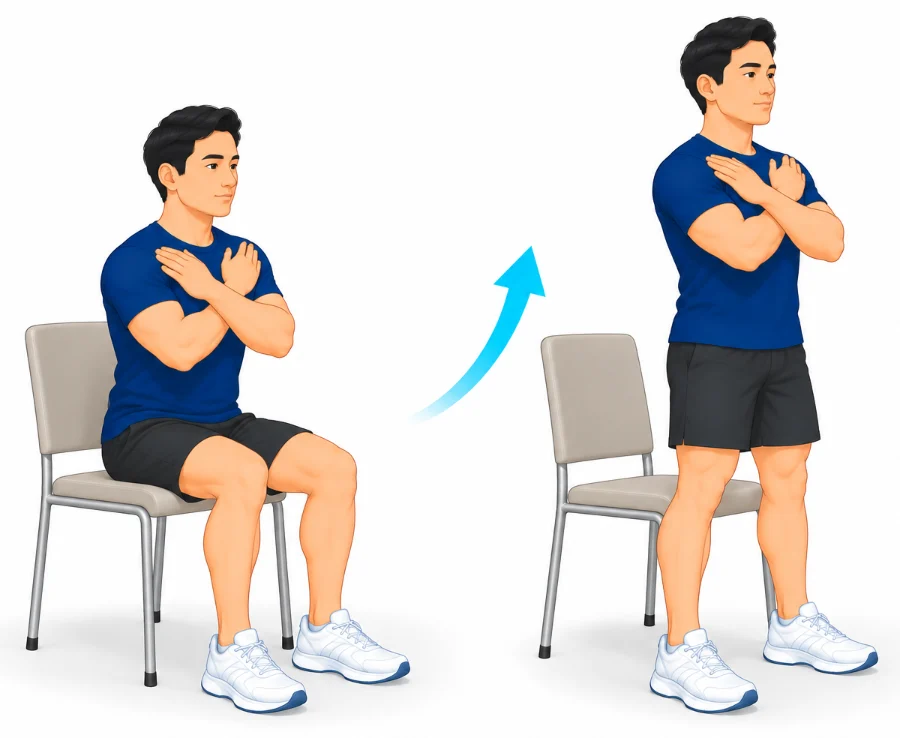
Sit to stand from a high chair
Sit on a higher firm chair or add a cushion. Lean forward and stand up, then sit down slowly. Lower the seat as it gets easier.
2 sets of 10, slow
Other treatment options
Medicines, taping and injections
Pain relief should be reviewed with your GP or pharmacist, taking your other health conditions and medicines into account. Taping or a knee sleeve may give short-term support. A corticosteroid injection may give temporary relief and help you keep exercising, but it does not restore cartilage.
When surgery is needed
In selected severe cases, knee replacement may be considered when pain and loss of function remain limiting despite a thorough strengthening program. A partial patellofemoral replacement may suit arthritis limited to the joint behind the kneecap, while a total knee replacement is used when other parts of the knee are also worn. Prof Phong Tran performs knee replacement, and his website explains the options and recovery.
Common questions
Is this the same as kneecap pain in younger people?
Not quite. Patellofemoral pain in younger, active people often occurs without cartilage wear. Patellofemoral arthritis means the cartilage behind the kneecap has worn, although both respond well to strengthening.
Should I avoid stairs and squats?
Reducing them for a time may help, but avoiding them completely can weaken the knee further. They are usually rebuilt gradually.
Does the grinding mean the knee is getting worse?
Not necessarily. Grinding under the kneecap is common and does not always match pain or damage.
Will exercise help if the cartilage is worn?
Often, yes. Stronger thigh and hip muscles help control how the kneecap is loaded, and many people notice less pain over several weeks to months.
When is surgery considered?
Only in selected severe cases where pain and loss of function remain limiting despite a thorough non-operative program.
Book an assessment
An assessment can confirm the diagnosis and set out a program that suits your knee and your daily activities. Physiotherapy with A/Prof Amir Takla and Imogen Clark, myotherapy with Joanne VanDer Haar, and specialist review with Prof Phong Tran, all at 166 Gipps Street, East Melbourne. Please bring any recent knee X-rays or scan reports and details of exercise already tried. Read about physiotherapy for kneecap pain.