
Osteoarthritis of the knee
Knee osteoarthritis is a common cause of knee pain, stiffness and swelling. It can make walking, stairs, getting up from a chair and sleeping harder, although symptoms vary a great deal between people. Many people stay active for years with the right exercise, pain relief and activity changes.
At the Specialist Orthopaedic Surgery Clinic in East Melbourne, orthopaedic assessment, physiotherapy, myotherapy and strength testing all happen in the same rooms, so your plan can be built around your knee and the activities you want to keep doing.

What is knee osteoarthritis?
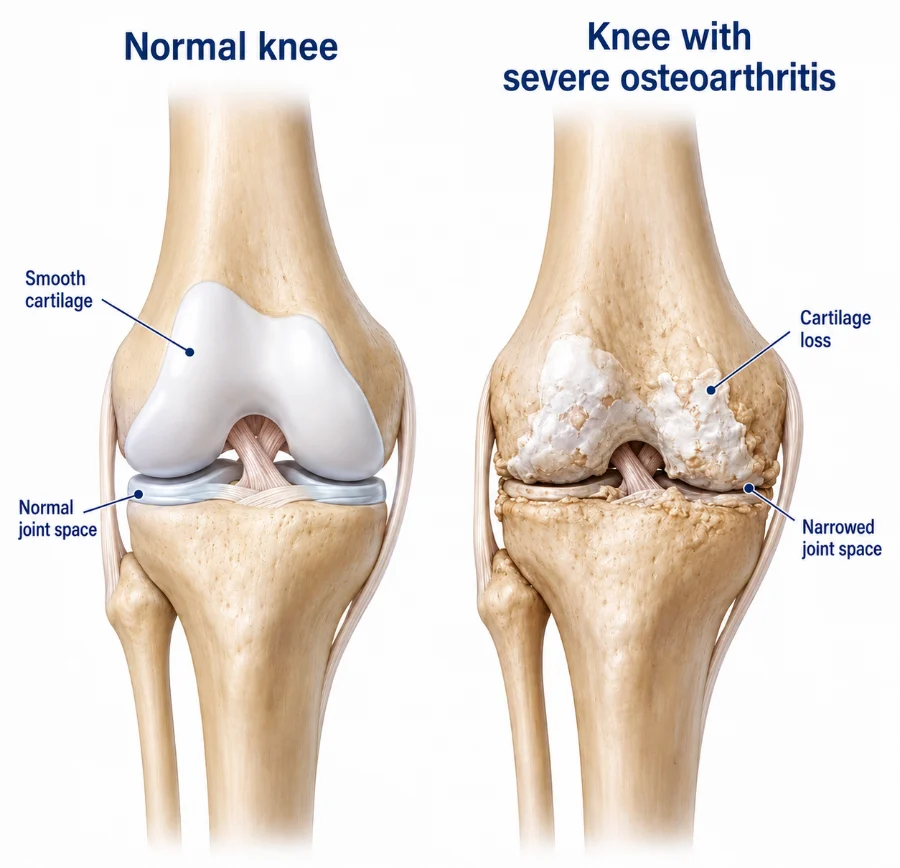
The knee joins the thigh bone, the shin bone and the kneecap. Smooth cartilage covers the joint surfaces so the bones glide easily, while the menisci, ligaments and muscles help the knee work well.
Osteoarthritis affects the whole joint. The cartilage thins, the bone changes shape and the knee can become stiff or swollen. It may affect one part of the knee or several, and the X-ray does not always match how the knee feels. It is not an inevitable part of getting older.
Does this sound like you?
Arrange an assessment if knee pain or stiffness is becoming more frequent, is limiting walking, stairs, work or sleep, or has not improved with a suitable exercise program. Review is also worthwhile if swelling keeps returning or you are relying more on pain medicines.
How it is diagnosed
Diagnosis starts with the pattern of pain, stiffness and swelling, and how the knee affects walking, stairs, sleep and daily tasks. Walking, alignment, movement, swelling, stability and muscle strength are all checked.
MRI is not routinely needed for established osteoarthritis. It may be considered when symptoms are unusual or another problem is suspected. Blood tests or a sample of joint fluid may be arranged if infection, gout or inflammatory arthritis is a concern.
Treatment and recovery
Treatment is matched to your symptoms, the activities you want to keep and your general health, and not to the X-ray alone. Most people start with education, exercise and physiotherapy, with pain relief and other supports added when needed.
First steps
Understand and pace
Learning about the condition and pacing walking, stairs and work so the knee stays active without long periods of rest.
Physiotherapy
Build strength
Quadriceps, hip and calf strengthening with mobility, balance and walking or cycling. Myotherapy can ease nearby muscles alongside exercise.
If pain limits progress
Settle flare ups
Pain relief reviewed with your GP or pharmacist. A brace, walking stick or injection may help some people keep exercising. Injections are not given at the clinic. If one is recommended, your GP can arrange it, usually through a radiology practice.
If symptoms stay severe
Review the plan
Strength and balance testing can track progress. Knee replacement may be discussed if pain and loss of function remain severe.
Exercises you may be given
Your physiotherapist will choose the right ones and the right level for you.
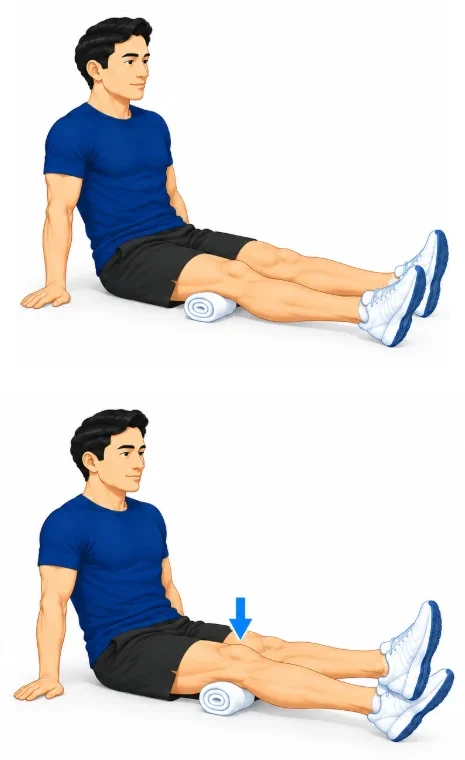
Quadriceps tightening
Sit with your leg straight and a rolled towel under the knee. Tighten the thigh muscle to press the back of the knee into the towel, hold, then relax.
10 holds of 5 seconds
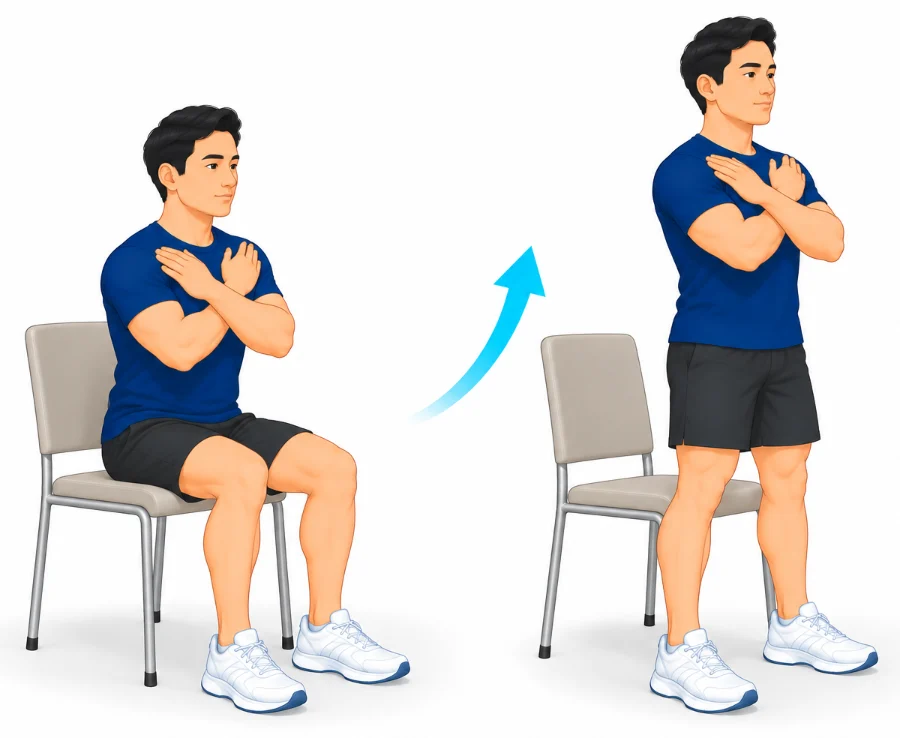
Sit to stand
Sit near the front of a firm chair with feet flat. Lean forward and stand up, then sit down slowly. Use your hands at first if needed.
2 sets of 10, slow
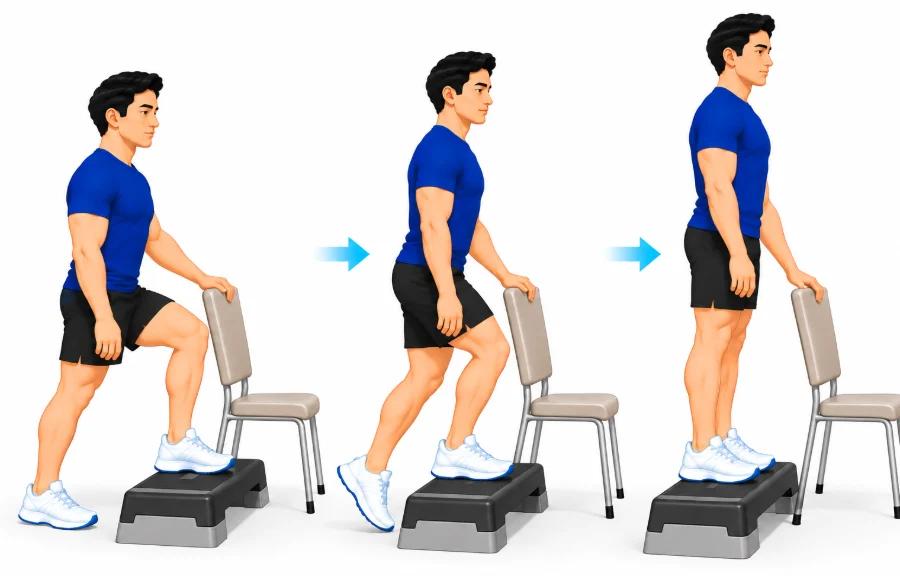
Step ups
Stand facing a low step with a rail or wall for balance. Step up with the sore leg, bring the other foot up, then step down slowly.
2 sets of 10
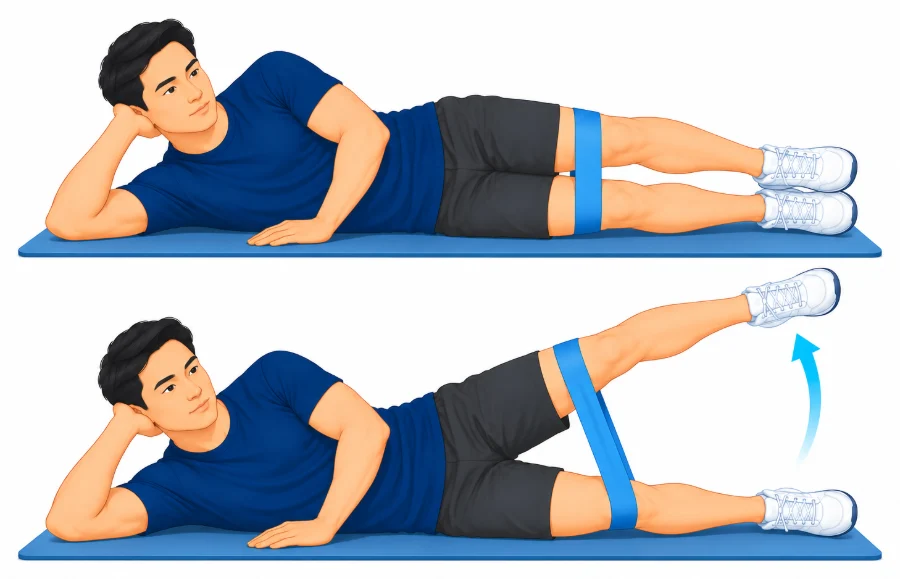
Side-lying leg lift
Lie on your side with the sore leg on top and the lower knee bent. Keep the top leg straight and lift it slowly towards the ceiling, then lower.
2 sets of 10 to 15
Other treatment options
Medicines, bracing and injections
Pain relief should be reviewed with your GP or pharmacist, taking your other health conditions and medicines into account. A brace or walking stick may help some people. A corticosteroid injection may give temporary relief and help you stay active, but it does not restore cartilage.
When surgery is needed
Partial or total knee replacement may be considered when pain, stiffness and loss of function substantially affect walking, sleep or independence despite suitable non-operative care. The X-ray appearance alone is not a reason for surgery, and arthroscopy does not treat widespread arthritis. Prof Phong Tran performs quadriceps-sparing knee replacement, and his website explains the options and recovery.
Common questions
Can knee osteoarthritis improve without surgery?
Yes. Exercise, physiotherapy, activity changes, weight management where relevant and pain relief can improve symptoms and function for many people.
Do I need an MRI?
Usually not. A standing X-ray and an examination normally give the most useful information. MRI is kept for unusual or uncertain cases.
Are knee injections a permanent fix?
No. Some injections may give temporary relief for selected people, but they do not reverse arthritis.
Will exercise wear the knee out faster?
Suitable exercise does not speed up arthritis. Stronger muscles help support the knee, and the program is adjusted to your symptoms.
When is knee replacement considered?
It may be discussed when pain and loss of function remain severe despite suitable non-operative care, and the examination and X-rays point to arthritis as the main cause.
Book an assessment
An assessment can confirm the diagnosis and set out treatment that suits your knee and your goals. Physiotherapy with A/Prof Amir Takla and Imogen Clark, myotherapy with Joanne VanDer Haar, and specialist review with Prof Phong Tran, all at 166 Gipps Street, East Melbourne. Please bring any recent knee X-rays, scan reports and a list of your current medicines.