
Rotator cuff tendinitis
Rotator cuff tendinitis, also called rotator cuff tendinopathy or subacromial bursitis, is a common cause of pain when lifting the arm, reaching overhead or lying on the sore shoulder. Most people improve with education, activity changes and a progressive exercise program.
At the Specialist Orthopaedic Surgery Clinic in East Melbourne, orthopaedic assessment, physiotherapy, myotherapy and strength testing all happen in the same rooms.

What is rotator cuff tendinitis?
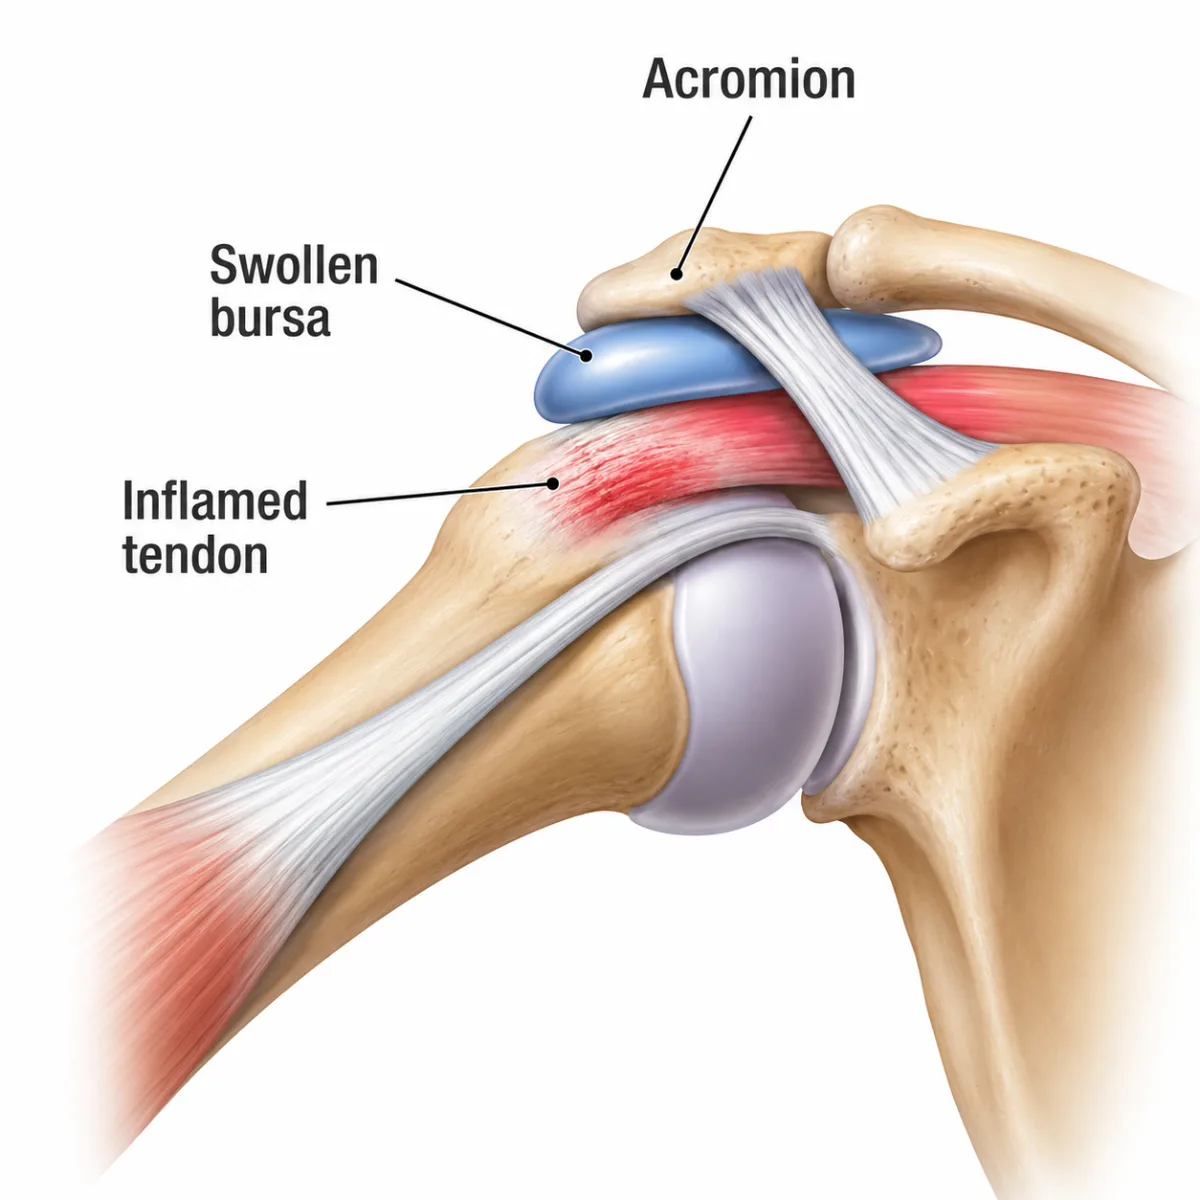
The rotator cuff is a group of tendons that help lift and control the arm. Rotator cuff tendinopathy means pain and reduced load tolerance in one or more of these tendons. The subacromial bursa, a nearby cushion, lets the tendons glide beneath the top of the shoulder, and the two often become painful together.
It usually develops when shoulder load increases faster than the tendons can adapt. Age-related tendon change, reduced strength and previous injury can also play a role. It does not always mean the tendon is torn, trapped or being permanently damaged, and most cases improve with the right load management and rehabilitation.
Does this sound like you?
Arrange an assessment if pain keeps returning, disturbs sleep, limits work or exercise, or has not improved with a structured exercise program, or if weakness or stiffness is increasing.
How it is diagnosed
Diagnosis is usually based on the pattern of pain and an examination of shoulder movement, strength and the neck. The clinician compares active and passive movement and checks which positions bring on the pain.
Imaging is not always needed. X-rays may be used after an injury or when arthritis is possible. Ultrasound or MRI may be used when symptoms persist, weakness is marked or the diagnosis is unclear.
Treatment and recovery
Non-operative care is the main treatment. The shoulder should stay active, while painful lifting, pressing or repeated overhead work is modified for a while. Each step starts when the one before it is going well, so the timing is a guide.
Weeks 1 to 2
Settle the pain
Adjust the activities that provoke pain. Keep the shoulder moving. Short-term pain relief can be reviewed with your GP or pharmacist.
Weeks 2 to 6
Restore movement
Physiotherapy begins loading the rotator cuff and shoulder blade muscles. Myotherapy can ease tight, overworked muscles alongside exercise.
Weeks 6 to 12
Build strength
Exercises progress to rebuild strength, movement control and tolerance for lifting and overhead work.
3 months onwards
Back to full activity
Return to work, gym or sport. VALD strength testing can measure your progress and find any gaps.
Exercises you may be given
Your physiotherapist will choose the right ones and the right level for you.

Pendulum swings
Lean on a bench and let the sore arm hang. Rock your body so the arm swings in small circles.
30 seconds, a few times a day

Outward press against a wall
Elbow bent and tucked in. Press the back of your hand into a door frame without moving. Hold, then relax.
5 holds of 30 to 45 seconds
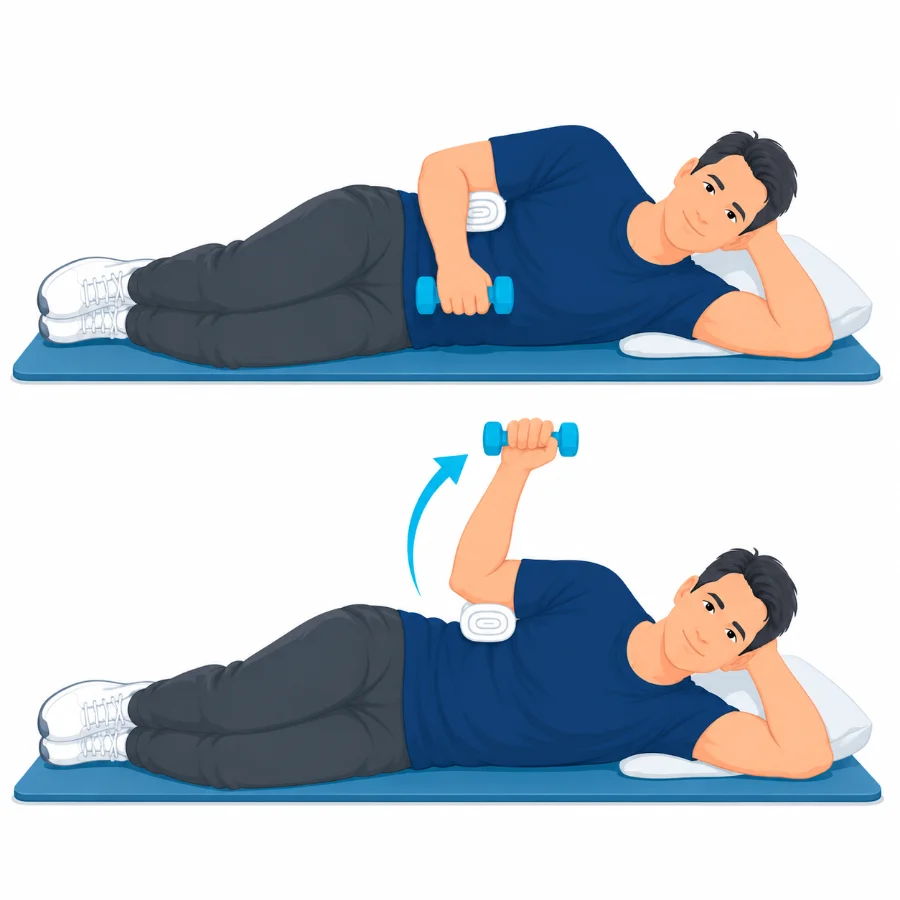
Side-lying rotation
Lie on your good side with a towel under the elbow. Slowly lift a light weight by turning the forearm up, then lower it.
3 sets of 10 to 15, slow
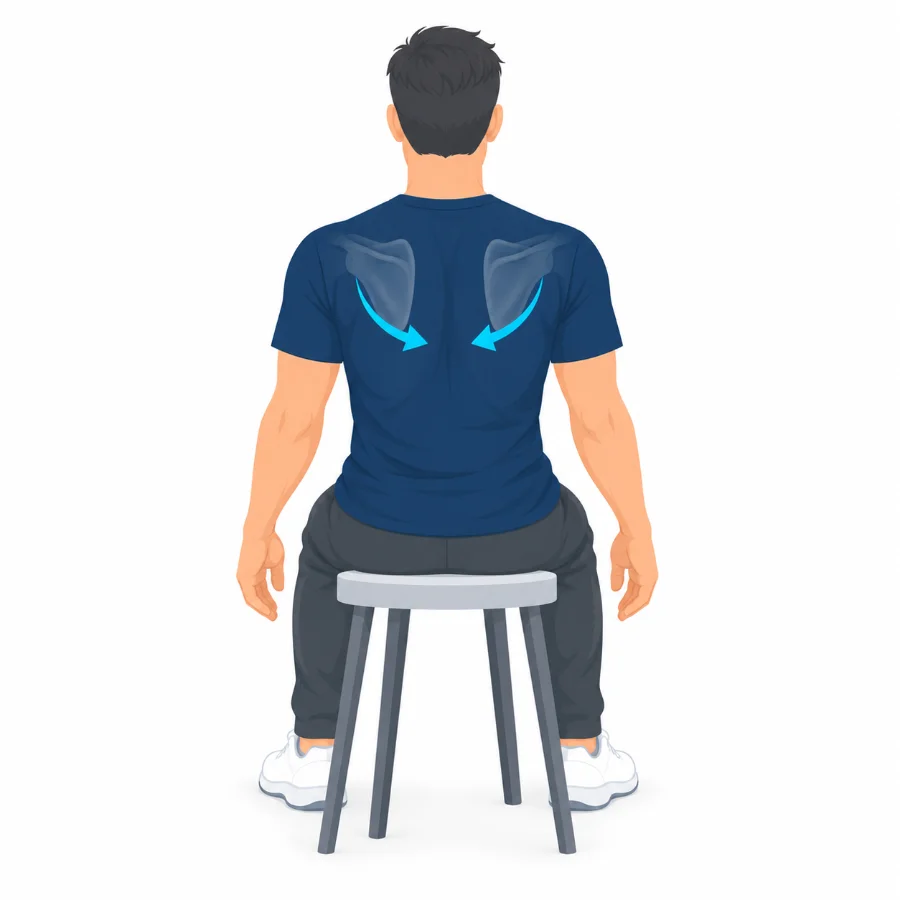
Shoulder blade squeeze
Sit or stand tall. Draw your shoulder blades gently back and down, hold, then relax. Keep your neck soft.
10 holds of 5 seconds
Other treatment options
Injections
Most people do not need one. A subacromial corticosteroid injection may help when pain is severe or stops useful rehabilitation. The benefit is usually temporary, and repeated injections are generally avoided. Read more about calcific tendinitis if there is calcium in the tendon. Injections are not given at the clinic. If one is recommended, your GP can arrange it, usually through a radiology practice.
When surgery is needed
Surgery is uncommon. It is considered only when symptoms remain substantial after a well-structured rehabilitation program and a separate treatable problem is found, such as a repairable tendon tear. If surgery is needed, Prof Phong Tran performs shoulder arthroscopy, and his website explains the operation and recovery.
Common questions
Is shoulder bursitis the same as a rotator cuff tear?
No. The bursa and tendons may be irritated without a full tear, although the conditions can occur together.
Should I avoid using the arm?
Complete rest is rarely needed. Painful overhead or heavy activity may be modified while movement and strength are rebuilt.
Do corticosteroid injections help?
They can give short-term relief for selected patients, particularly when pain prevents useful rehabilitation.
Do I need an MRI?
Usually not at first. Ultrasound or MRI is considered when weakness is marked, symptoms persist or another condition is suspected.
Is it the same as impingement?
They overlap. Impingement was the older name, based on the idea of the tendon being pinched. Pain is not always caused by a tendon being trapped, and both are treated the same way.
Book an assessment
Physiotherapy with A/Prof Amir Takla and Imogen Clark, myotherapy with Joanne VanDer Haar, VALD strength testing and specialist review with Prof Phong Tran, all at 166 Gipps Street, East Melbourne. Bring details of previous physiotherapy, medicines or injections. Read about physiotherapy for rotator cuff problems.